SMAS vs. Deep Plane Facelift: The Difference That Actually Matters
Deep plane or SMAS? Neither facelift suits every face. How the two differ in depth, risk and recovery, for patients weighing facelift surgery in Korea.
PK
Peep Korea Editorial · 17 min read
Short answer
SMAS and deep plane are both facelifts that move deeper tissue than skin alone. SMAS is often used for the lower face and jawline; deep plane targets midface descent and works closer to facial nerve branches. Two large 2025 reviews did not find one technique better overall, so the assessment of your own face matters more than the name of the operation.1, 2
Neither facelift wins, and that turns out to be the key thing to understand about this entire debate. Two large recent reviews of the evidence have declined to crown one technique.1, 2 What matters enormously is something much less exciting than the name of the operation: your face - and the surgeon operating on it.
Deep Plane has become the celebrity of the facelift world: it sounds newer, more sophisticated and, obviously, deeper. SMAS, meanwhile, has been around for decades. It's the dependable veteran, less glamorous perhaps, but still a widely used foundation of modern facelift surgery. That is why so many people assume there must be a winner.
What is the difference between SMAS and deep plane facelift?
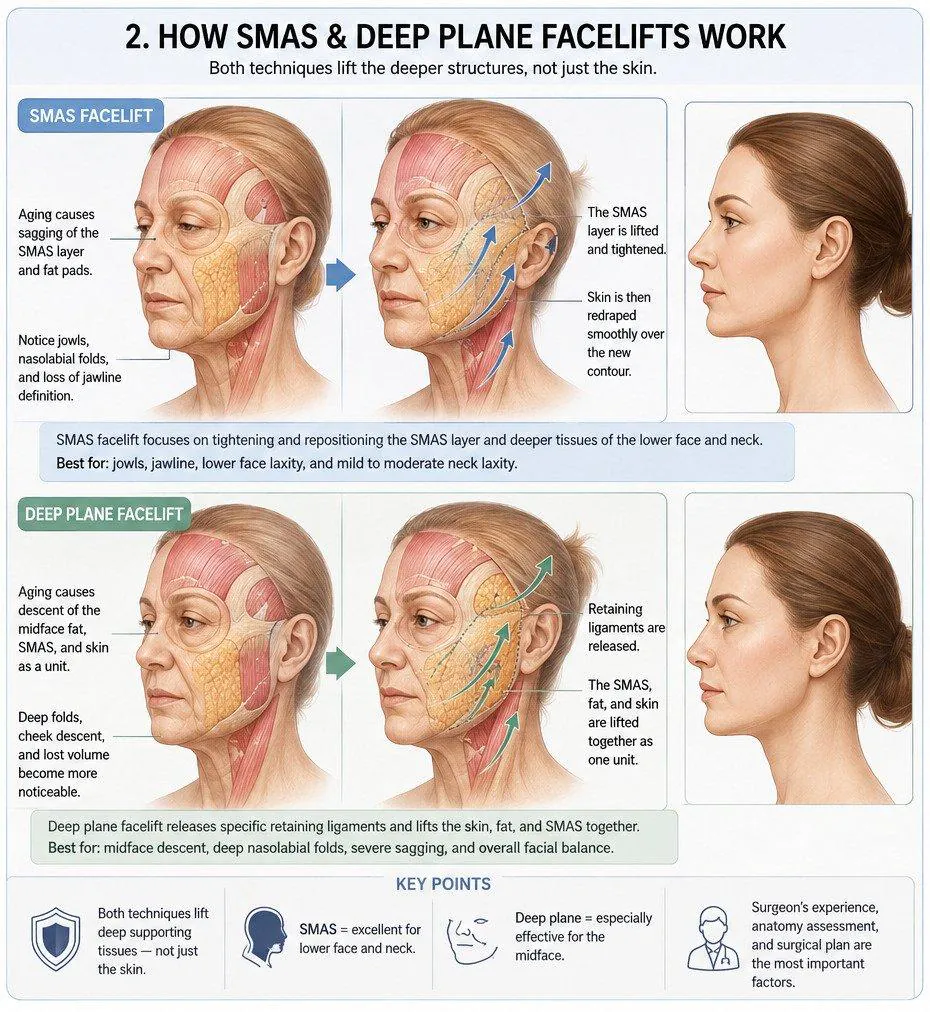
Both operations move the deeper face, not only the skin. The difference is what the surgeon releases and which part of the face the lift is aimed at. A SMAS facelift tightens, folds or repositions the SMAS layer and suits the lower face; a deep plane facelift releases retaining ligaments so skin, fat and SMAS move as one unit, and suits the midface.
Satisfaction and complication figures: Khoury et al., Aesthetic Plastic Surgery, 2025 - a meta-analysis of 21 studies and 2,896 patients. Longevity figure: Levin & Frankel, Facial Plastic Surgery & Aesthetic Medicine, 2026. These are pooled averages across many surgeons, not predictions for any individual patient.
SMAS facelift
Deep Plane facelift
What moves
The SMAS layer is tightened, folded, or repositioned
Retaining ligaments are released so skin, fat, and SMAS move as one unit
Aimed at
Lower face - jawline, jowls, lower cheeks
Midface - cheek descent, deep nasolabial folds
Technical difficulty
Well established, widely performed
More demanding; works closer to facial nerve branches
Reported satisfaction
87.8%
94.4%
Reported complication rate
10.3%
17.2%
Typical longevity
Long-term comparative data is limited
Mean 10.9 years to revision in one 30-year series
Often used for
Mild-to-moderate lower-face aging
Significant midface descent and advanced laxity
To understand why neither wins, we first need to talk about something many of us misunderstand: aging.
Your skin isn't really the problem
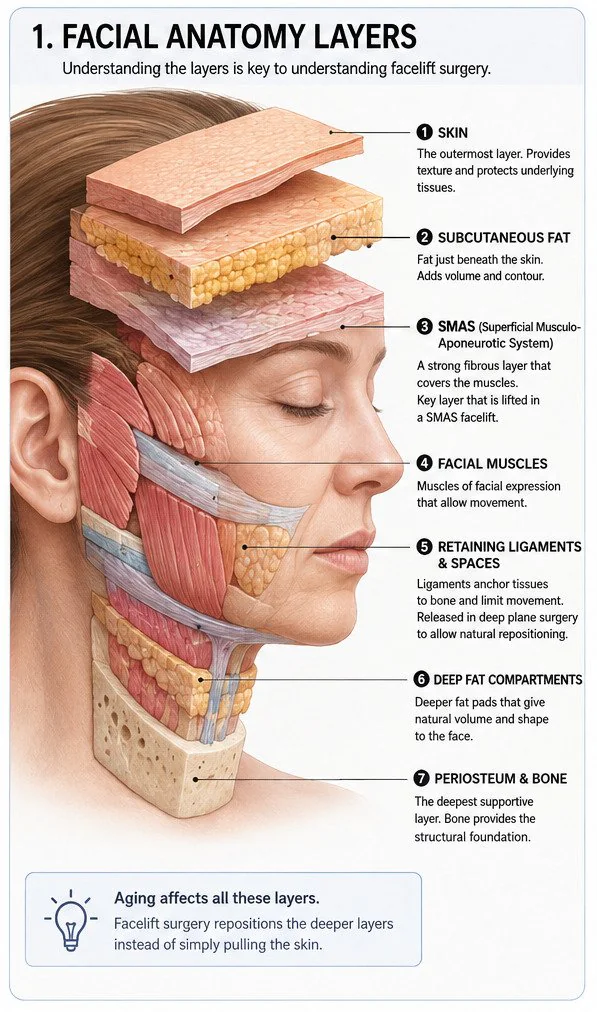
Your skin is only the outer layer of the problem. Look in the mirror and pinch your cheek: if your face has begun to sag, it's tempting to think the obvious thing has happened and your skin became loose. That explanation is simple, and it's incomplete. Your face is more like a building than a sheet of fabric, and what you see on the outside depends on an entire structure underneath it.
As we age, the skin becomes thinner and loses some of its collagen and elastin. Fat disappears from some areas and shifts downward in others. The ligaments holding facial tissues in place begin to stretch. The connective layer known as the SMAS loosens. Even the bones underneath your face slowly change: the scaffolding itself is aging.4, 5
Illustration: the layered structure of the face. Modern facelift surgery repositions the deeper layers rather than pulling the skin tighter. Individual anatomy varies.
That combination creates the things we eventually notice in photographs: cheeks sitting lower than they used to, deeper smile lines, jowls appearing along the jaw, a softer jawline, loose neck skin and a more hollow-looking midface. And once surgeons understood that, facelift surgery changed.
The old facelift had a fairly obvious problem
The old facelift asked the skin to do a job it wasn't designed to do: hold up the entire aging face. Decades ago, a facelift could be surprisingly literal. Loose skin? Pull it tighter. Surgeons would tighten the skin and remove the excess, and that could create the classic "windswept" facelift look.
Modern facelift surgery works differently. Instead of asking the skin to carry everything, surgeons reposition the deeper structures underneath it. Once those structures are back where they belong, the excess skin can be removed without having to pull the face unnaturally tight.
Think about remaking a bed. If the bedsheet is wrinkled because the mattress underneath has shifted, aggressively pulling one corner of the sheet isn't really solving the problem. Fix what's underneath first. That, essentially, is the philosophy behind both SMAS and Deep Plane facelifts, and this is where the two procedures finally part ways.
Meet the SMAS facelift
A SMAS facelift lifts the support layer under the skin, not just the skin. First, the terrible name: SMAS = Superficial Musculoaponeurotic System. You absolutely do not need to remember that. What you should remember is that the SMAS is a strong layer of connective tissue and muscle underneath your skin, like a flexible support mesh running through much of the face and neck.
Your skin and facial fat essentially have this deeper support system underneath them, and as that support system descends with age, your face descends with it. So a SMAS facelift doesn't simply pull the skin upward. The surgeon typically makes incisions hidden around the ears and hairline, lifts the skin and then works on the SMAS underneath. Depending on the technique and the patient's anatomy, the SMAS may be tightened, folded - called plication - or repositioned.
Then the skin is redraped naturally over the newly repositioned structure, the excess is removed and the incisions are closed. The important word here is support: the deeper layer is carrying the lift, not the skin. That's one reason a well-executed SMAS facelift shouldn't make someone look as though their face has been pulled toward their ears.
It can be particularly effective for the lower face: early or moderate jowls, a fading jawline, sagging lower cheeks and moderate neck laxity. For many people experiencing mild-to-moderate facial aging, particularly those in their 40s through 60s, it can offer a very useful combination of predictability, effectiveness and safety. Then somebody asked: what if we go deeper?
Enter the Deep Plane
A Deep Plane facelift goes underneath the SMAS instead of only working on it. There are structures in your face called retaining ligaments, little anchor points holding facial tissue in position. In Deep Plane surgery, the surgeon carefully releases certain ligaments so that the skin, fat and SMAS can move together as one unit.
Here's another way to picture it. Imagine a blanket lying on a bed. With one approach, you're adjusting and tightening a particular layer. With the other, you're freeing the blanket from the places where it's caught and moving the entire thing together. That's the central idea behind the Deep Plane facelift, and it gives the technique an interesting advantage.
Illustration: how each technique repositions tissue. This is a simplified teaching diagram, not a depiction of expected results - individual outcomes vary.
The Deep Plane's favorite territory: the middle of your face
The midface is where the Deep Plane technique tends to help. It is one of the harder areas to rejuvenate: the cheeks descend, the fold running from the nose toward the mouth - the nasolabial fold - becomes deeper, and volume seems to migrate downward. Because the Deep Plane technique releases retaining ligaments and moves the tissue together, surgeons can reposition this area while placing relatively little tension on the skin.
That's why Deep Plane surgery has developed such a strong reputation for improving drooping cheeks, deep nasolabial folds, midface descent and overall facial balance. SMAS, meanwhile, is particularly strong in the lower face: jawline, jowls, lower cheeks and lower-face laxity. This sounds like an easy victory for Deep Plane, except there's a catch, and a rather important one.
Deeper also means harder
Deep Plane surgery operates closer to important facial nerve structures and requires considerably more anatomical knowledge and technical experience. Those nerves are responsible for making your face… your face: smiling, frowning, moving your mouth, and making the expression you make when someone tells you a Deep Plane facelift is automatically better because it costs more.
The learning curve is steep. That's why the surgeon's experience with this specific operation matters enormously, and here we arrive at a common misconception in the SMAS-versus-Deep-Plane debate.
"Which one looks more natural?"
Either can: both SMAS and Deep Plane surgery can produce extremely natural results when they're performed well. Almost everyone considering a facelift eventually asks some version of the same question, "Am I going to look like I've had a facelift?" It's understandable. Many people don't want a new face; they want their old face back.
Deep Plane gets plenty of attention because the technique minimizes tension on the skin. That's a real advantage. But natural-looking isn't a proprietary feature of Deep Plane surgery. A superb SMAS facelift can look remarkably natural, and a badly executed Deep Plane facelift does not become beautiful simply because the words Deep Plane appear on the clinic's website. The technique matters; the person performing it matters more.
Which facelift lasts longer, SMAS or deep plane?
Neither has been shown to last longer. You'll sometimes see claims that Deep Plane surgery lasts dramatically longer, but the research is much less dramatic. The main long-term data comes from a 2026 review of thirty years of deep plane facelifts by a single surgeon. Among the patients who came back for a second lift, the average gap between the first and second operation was 10.9 years.3
Interestingly, age at the time of the first surgery mattered. Patients who had their first deep plane facelift at 53 or younger went an average of 12.4 years before returning. Those over 53 came back after 9.3 years.3
Two things are worth noticing about that number. First, it describes people who chose to have a second facelift. It isn't a measurement of when results "expire" - plenty of people never come back at all. Second, equivalent long-term comparative data for SMAS facelifts is thinner than the internet suggests. Anyone telling you confidently that one technique outlasts the other by a specific number of years is telling you more than the evidence currently supports.
Why is this so hard to pin down? Because surgery doesn't stop biology. You leave the operating room younger-looking; you don't leave immortal. Your face continues to age according to your genetics, skin quality, sun exposure, smoking history, lifestyle, weight changes and health, and once again, surgical technique and surgeon skill matter.
So who tends to choose SMAS?
People whose main concern is the lower face. Imagine someone whose complaint is, "My jawline is disappearing." They have mild-to-moderate sagging around the cheeks and jaw, early jowls, some neck laxity, but reasonably good skin elasticity. That can be an excellent SMAS candidate.
Many patients fall somewhere in their late 40s to 60s, but that age range can be misleading. Surgeons don't operate on birthdays; they operate on anatomy. A 47-year-old and a 57-year-old can have completely different facial structures, skin quality and degrees of tissue descent.
And who tends to choose Deep Plane?
People whose problem sits higher, in the midface. Now imagine the cheeks have descended noticeably, the nasolabial folds are deep, and there are obvious jowls and substantial midface sagging. That is where Deep Plane may become especially attractive. But again, age doesn't automatically decide it.
A younger patient with significant inherited tissue descent could potentially benefit from Deep Plane surgery, while an older patient with a different facial structure might be better suited to SMAS. The mirror doesn't care what year you were born.
Does your ethnicity change the answer?
It can. Facial anatomy differs meaningfully between individuals and between populations - skin thickness, fat distribution, bone structure, and the way tissue descends over time are not identical across every face. A technique refined largely on one kind of anatomy doesn't automatically transfer to another. This question gets asked constantly and answered rarely.
For patients traveling to Korea, this is worth asking about directly. A surgeon who performs hundreds of facelifts a year may still have performed relatively few on patients with anatomy like yours. The question to ask is not "Do you do deep plane facelifts?" It's "How many facelifts have you performed on patients with a facial structure similar to mine, and can I see those results?"
Now for the part nobody likes talking about: complications
Both techniques carry real risks. A facelift is elective, but it is still surgery: SMAS and Deep Plane facelifts both carry potential complications, including hematoma, visible scarring, slow wound healing, skin necrosis, temporary nerve weakness and, rarely, permanent nerve injury affecting facial movement. There's also something called pixie ear deformity, where tension pulls the earlobe downward into an elongated appearance.
Smoking matters too, because it increases the risk of poor healing and tissue problems. That's one reason surgeons can be so strict about stopping nicotine before surgery.
And here the data gets genuinely interesting. A 2025 meta-analysis pooling 21 studies and 2,896 patients found that Deep Plane facelifts produced higher patient satisfaction - 94.4% versus 87.8% for SMAS - but also a higher overall complication rate, 17.2% versus 10.3%.1
Read that twice, because it's the honest shape of this whole debate. Deep Plane isn't the technique that beats SMAS. It's the technique that asks for more and, in experienced hands, can give more back. More satisfaction, more risk. That is a trade-off, not a verdict.
A separate 2025 meta-analysis - larger still, at 47 studies and 10,766 patients - concluded that both approaches show comparable safety profiles, and that the available comparative data isn't strong enough to declare one technique more effective than the other.2 Two large reviews, two research teams, and neither willing to name a winner. That should tell you something about how confident the surgeon promising you a winner really ought to be.
What does facelift recovery feel like?
Swollen, bruised and tight at first, then better sooner than many people expect, with the final result taking months. Let's get rid of the glamorous Instagram version: you will probably not leave facelift surgery looking mysteriously 15 years younger and head directly to dinner. Recovery timing drawn from the guide body (individual courses vary):
When
What recovery usually feels like
Week 1
Swelling and bruising most prominent; rest; head elevated
Weeks 2–3
Much visible bruising fades; many return to light office or social plans
Month 1
Substantial improvement visible; not the final result
Months 6–12
Tissues settle toward the longer-term look
The first week is generally the hard part. You'll swell, you'll bruise and your face may feel tight. Swelling and bruising are prominent, rest matters, sleeping with your head elevated is commonly recommended and strenuous activity is off the menu. Then things begin moving surprisingly quickly: by around two to three weeks, much of the visible bruising has faded and many patients feel comfortable returning to office work or light social activities.
But that is not the final result. Residual swelling can hang around for months. You'll usually see substantial improvement during the first month, while complete settling of the tissues can take roughly six to twelve months. During that period, your surgeon may tell you to avoid smoking, strenuous exercise, heavy lifting and excessive sun exposure. This is one situation where improvisation is not particularly clever: follow the postoperative instructions.
A careful facelift may be the one nobody notices
The more successful the operation, the less likely people are to recognize that an operation happened. That's an interesting paradox in cosmetic surgery. A good facelift doesn't freeze your face in time; it repositions aging tissue and gives you a younger starting point from which you continue aging normally.
The ideal reaction isn't necessarily "Wow! Amazing facelift!" It's more like "You look really good. Did you lose weight? Were you on vacation?" That's the point.
And sometimes a facelift alone isn't enough to create that balance. Depending on the face, surgeons may combine it with a neck lift, brow lift, eyelid surgery (blepharoplasty), fat grafting, chin or cheek implants, or rhinoplasty.
That doesn't mean everyone needs a shopping cart full of procedures. It means faces age as systems, and sometimes treating several parts together produces a more harmonious result. And if your concerns are more about skin quality than structure, the non-surgical route may fit better - see 7 Korean Skin Treatments, Explained.
And then there's Korea
People increasingly travel for facial surgery, and South Korea has become a major destination, drawing patients from across Asia, North America, Europe, Australia and the Middle East. But "Korea is good at plastic surgery" is not useful information when you're choosing a surgeon. Here is what actually matters if you're considering the trip.
The credential most foreign patients never check
In Korea, a licensed doctor can list plastic surgery as a clinic department. 성형외과 전문의, the plastic surgery specialist title, is a different and narrower qualification that follows residency training. Both may advertise in English as a "plastic surgeon."
Ask whether your surgeon holds 성형외과 전문의 certification, and ask to see it. How to check it from abroad, along with the clinic, the consent form and where to get help, is in our Korea surgery safety and verification guide.
Volume is real, but ask about your operation
High-volume practice does matter in technically demanding surgery, and many Seoul clinics do perform large numbers of facial procedures. But volume in double-eyelid surgery tells you nothing about facelift experience. Ask specifically: how many deep plane facelifts, or SMAS facelifts, has this surgeon performed - not the clinic.
What it costs
We have not found a neutral, dated source for Seoul facelift prices, so this guide does not print one. The cost hub shows the published US surgeon's fee and the lines a Korean quote can leave out. Ask for an itemized won quote that names the technique, and remember the clinic sets the final price.
The question that actually matters for a trip
A facelift is not a procedure you fly home from in three days. Ask before you book: how long do you need to stay, when can you fly, and - above all - who handles it if something goes wrong after you've left the country? If a clinic can't answer that last question clearly, that's a walk-away signal, in Seoul or anywhere else.
Flying to Korea doesn't magically make an operation good. The same rule applies here as everywhere: choose the surgeon, not the marketing.
So which facelift wins?
Neither wins in general; the better facelift is the one that fits your face. If you have moderate lower-face aging and want a proven, predictable operation, a SMAS facelift may make perfect sense. If your main issue is significant midface descent, deep folds and advanced tissue sagging, a Deep Plane facelift may offer advantages.
So stop asking "Which facelift is better?" and ask "Which facelift is better for my face?" That's a very different question, and it can't be answered by TikTok, Reddit, a clinic advertisement - or this article. It requires someone to examine your facial anatomy, skin quality, tissue laxity, medical history and goals.
The thing worth remembering
SMAS vs. Deep Plane probably shouldn't be a competition, even though the internet has turned it into one. Both represent the same major advancement over old skin-only facelifts: don't simply pull the covering tighter; reposition the structure underneath it. Deep Plane has particular strengths in the midface, SMAS remains an established and reliable approach to facial rejuvenation, and neither is universally superior.
So if you're considering a facelift - in Korea or anywhere else - spend less time asking whether a surgeon offers the technique of the moment and more time asking harder questions:
How many of these operations have they performed?
Can you see before-and-after photographs of people with anatomy similar to yours?
What complications do they see?
Why are they recommending this technique for your face?
And what would they recommend if the words SMAS and Deep Plane disappeared from the marketing material entirely?
Because ultimately, the decision that matters isn't which facelift you choose. It's who you trust to choose it with you.
Quick FAQ
Not established. The main long-term series found an average of 10.9 years before a second lift among deep plane patients who returned for one, but comparable long-term SMAS data is limited, and no study has demonstrated a universal longevity winner.3
No. Pooled data found a higher overall complication rate for deep plane (17.2% vs 10.3%), while a larger review concluded both have comparable safety profiles. Both can be performed safely by experienced, board-certified surgeons - but deep plane is technically more demanding and works closer to important structures.
Either one. Planning and surgeon skill matter more than the acronym on the procedure name.
Yes. They're more common in the 40s–60s, but anatomy matters more than age. Younger people with hereditary laxity or early tissue descent may also be candidates. There's some evidence that operating earlier is associated with longer-lasting results.
Incisions are generally positioned around the ears and within the hairline where possible. With appropriate healing and scar care, they typically become increasingly difficult to notice over the following months.
Yes. Neck lifts, brow lifts, eyelid surgery, fat grafting, implants and rhinoplasty are common combinations when appropriate.
Ask directly whether the surgeon holds 성형외과 전문의 (plastic surgery specialist) status, and ask to see the certificate. The full set of checks, from the clinic sign to the consent form, is in our safety and verification guide.
Showing 5 of 7
Medical note
This article is for general education and is not medical advice, a diagnosis, or a promise of outcome. Technique names and published series are discussed to explain categories, not to endorse a clinic or guarantee a result. Facelift plans depend on anatomy, surgeon training, and medical history; speak to a board-certified plastic surgeon before any operation.
This article is general health information for educational purposes. It is not medical advice, diagnosis, or treatment. Always consult a qualified physician about your individual situation.
Khoury A, et al. The Deep Plane versus SMAS Facelift: A Systematic Review and Meta-Analysis.Aesthetic Plastic Surgery, 2025. Meta-analysis of 21 studies, 2,896 patients. Link
Vayalapra S, Guerero DN, Sandhu V, et al. Comparing the Safety and Efficacy of Superficial Musculoaponeurotic System and Deep Plane Facelift Techniques: A Systematic Review and Meta-analysis.Annals of Plastic Surgery, 2025. 47 studies, 10,766 patients. PubMed
Levin M, Frankel A. Thirty Years of Deep Plane Facelifts: Characterizing Outcomes and Longevity.Facial Plastic Surgery & Aesthetic Medicine, 2026. Link
Decoding Skin Aging: A Review of Mechanisms, Markers, and Modern Therapies.Cosmetics (MDPI), 2025. Link
Facial skin ageing: Key concepts and overview of processes.International Journal of Cosmetic Science (Wiley). Link